
GLP-1 Medications: Uses, Effects, and Questions Before Treatment

GLP-1 receptor agonists can help treat type 2 diabetes or obesity, depending on the medicine and its approved use. They act on pathways involved in blood sugar, appetite, and digestion. A prescription should match the condition you need to treat rather than the popularity of a brand name.
These medicines can provide substantial benefit for suitable patients, but they require a plan for dose changes, side effects, nutrition, and follow-up. They do not replace an assessment of the reasons for weight gain or poor glucose control.
What the GLP-1 signal does
The intestine releases glucagon-like peptide-1 after eating. This hormone participates in signals that regulate blood sugar and appetite. A GLP-1 receptor agonist activates the relevant receptors, helping the body release insulin when glucose rises and influencing other processes involved in glucose control.
The medicine can also slow stomach emptying and affect brain pathways that help regulate hunger and fullness. Someone may feel satisfied after a smaller amount of food or notice less persistent interest in eating. The extent of that change differs between people.
The drug does not simply force the body to make more natural GLP-1. It mimics part of the hormone's activity at a receptor. Nor does reduced appetite establish that you receive enough fluid, protein, or other nutrients; those needs remain part of care.
Diabetes treatment and weight treatment are different indications
A clinician may choose a GLP-1 medicine to improve glucose control in type 2 diabetes, particularly when the person's weight or other health conditions influence the choice. They consider the full diabetes plan, including other glucose-lowering medicines and the risk of low blood sugar.
For chronic weight management, the product must fit the person's medical circumstances and prescribing criteria. Assessment commonly considers body mass index, weight-related conditions, previous treatment, and potential benefit. BMI provides one part of that assessment rather than a complete account of health.
A diabetes product can contain the same active ingredient as a weight-management product while having different approved uses, doses, devices, and instructions. Do not switch products or translate a dose yourself because the generic name looks familiar.
Food, activity, sleep, and behavioral support can work alongside medication. Requiring someone to repeat unsuccessful diets indefinitely is different from assessing the role of treatment, just as prescribing a medicine without support can overlook practical barriers to sustained care.
Examples within and alongside the drug class
Semaglutide and liraglutide are GLP-1 receptor agonists. Familiar products include Ozempic and Wegovy for semaglutide, and Victoza and Saxenda for liraglutide. The specific product determines the authorized use and instructions; a name alone does not establish suitability.
Common injectable semaglutide regimens use weekly dosing, while injectable liraglutide regimens use daily dosing. Oral semaglutide products also exist and have their own administration requirements. Confirm the formulation instead of assuming that all products with one ingredient follow one schedule.
Tirzepatide acts on both GIP and GLP-1 receptors. It belongs in a related treatment discussion, but calling every medicine a pure GLP-1 agonist hides a difference in mechanism. Product-specific benefits and precautions still need review.
Combination use requires medical direction. Taking two products containing semaglutide, or adding another medicine in the same pathway, can increase risk without providing a safe shortcut to better results.
What to expect from weight change
Weight change usually develops over time rather than after the first dose. Clinicians often increase doses gradually to improve tolerability, so the starting dose may not represent the intended maintenance treatment. Do not accelerate that schedule because early change seems slow.
Clinical trials report averages for particular products, doses, populations, and periods. An average cannot promise your result or make one study directly comparable with another. Some participants respond more, some less, and some stop because of adverse effects or other barriers.
A useful follow-up includes appetite, eating adequacy, glucose where relevant, side effects, function, and health goals as well as weight. A rapid drop accompanied by persistent vomiting or inability to eat is a reason to contact the clinician, not a result to pursue.
Ask what treatment would look like after an initial response. Obesity often requires ongoing management, and stopping medicine can allow appetite and weight to rise again. Discuss affordability and access early so a gap does not force an unplanned change.
Digestive effects are common but deserve attention
Nausea, vomiting, diarrhea, constipation, abdominal discomfort, and fullness can occur. Symptoms often appear when treatment begins or the dose increases. Smaller meals and an approach that respects early fullness may help some people, but severe or persistent symptoms need review.
Repeated vomiting or diarrhea can lead to dehydration and worsen kidney function. Tell the clinician if you cannot keep fluids down, urinate less than usual, or feel increasingly weak or dizzy. Do not simply wait for the next scheduled dose increase.
A clinician may adjust timing, slow the escalation, evaluate another cause, or change treatment. Follow their instructions rather than skipping and restarting at a high dose. A long interruption may require a different restart plan from one missed dose.
Recognize the problems that need prompt care
Severe persistent abdominal pain, particularly with vomiting or pain extending toward the back, needs assessment for conditions such as pancreatitis. Upper abdominal pain, fever, or yellowing skin can also require evaluation for a gallbladder or liver-related problem.
Low blood sugar becomes more likely when certain GLP-1 treatments accompany insulin or medicines such as sulfonylureas. Ask whether another diabetes dose needs adjustment and how to recognize and treat a low glucose episode. Do not stop insulin without a specific plan.
People with diabetes should discuss a history of retinopathy and report new vision symptoms. Improvements in glucose control and product-specific effects can complicate eye care, so routine follow-up and symptom reporting matter.
Breathing difficulty, throat or facial swelling, or another severe allergic reaction needs urgent help. A concerning symptom deserves assessment even if it does not appear on a short list of common side effects.
Understand the thyroid warning accurately
Some medicines in this group carry a boxed warning about thyroid C-cell tumors based on findings in rodents. Researchers have not established that the same tumor risk occurs in humans. That uncertainty differs from saying that the medicine has proved to cause an inherited thyroid cancer in patients.
For affected products, a personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia syndrome type 2 rules out treatment. These specific diagnoses differ from every thyroid nodule, an underactive thyroid, or a relative's unspecified thyroid problem.
Provide the actual family diagnosis if you know it and ask the clinician to clarify uncertain records. Report a neck lump, persistent hoarseness, or swallowing problems rather than assuming that a blood test alone resolves every concern.
Bring the full medical history to the decision
Discuss previous pancreatitis, gallbladder disease, kidney problems, severe stomach-emptying symptoms, diabetes complications, and any prior reaction to a related medicine. Some histories call for caution or another option; they do not all create the same blanket contraindication.
Inflammatory bowel disease does not automatically rule out every GLP-1 medicine. The clinician needs the diagnosis, current symptoms, other treatment, and the specific product under consideration. Severe gastroparesis presents a separate concern that should not be confused with all bowel conditions.
Weight-loss treatment does not belong in pregnancy. Tell the prescriber about pregnancy, pregnancy plans, or breastfeeding before treatment, because stopping intervals and alternatives depend on the product. Do not use a general online waiting period for every medicine.
Tell surgical and anesthesia teams that you take a medicine that can delay stomach emptying. They need that information to plan care around the procedure and your symptoms. Do not create your own interruption schedule without their advice.
Use the actual product instructions
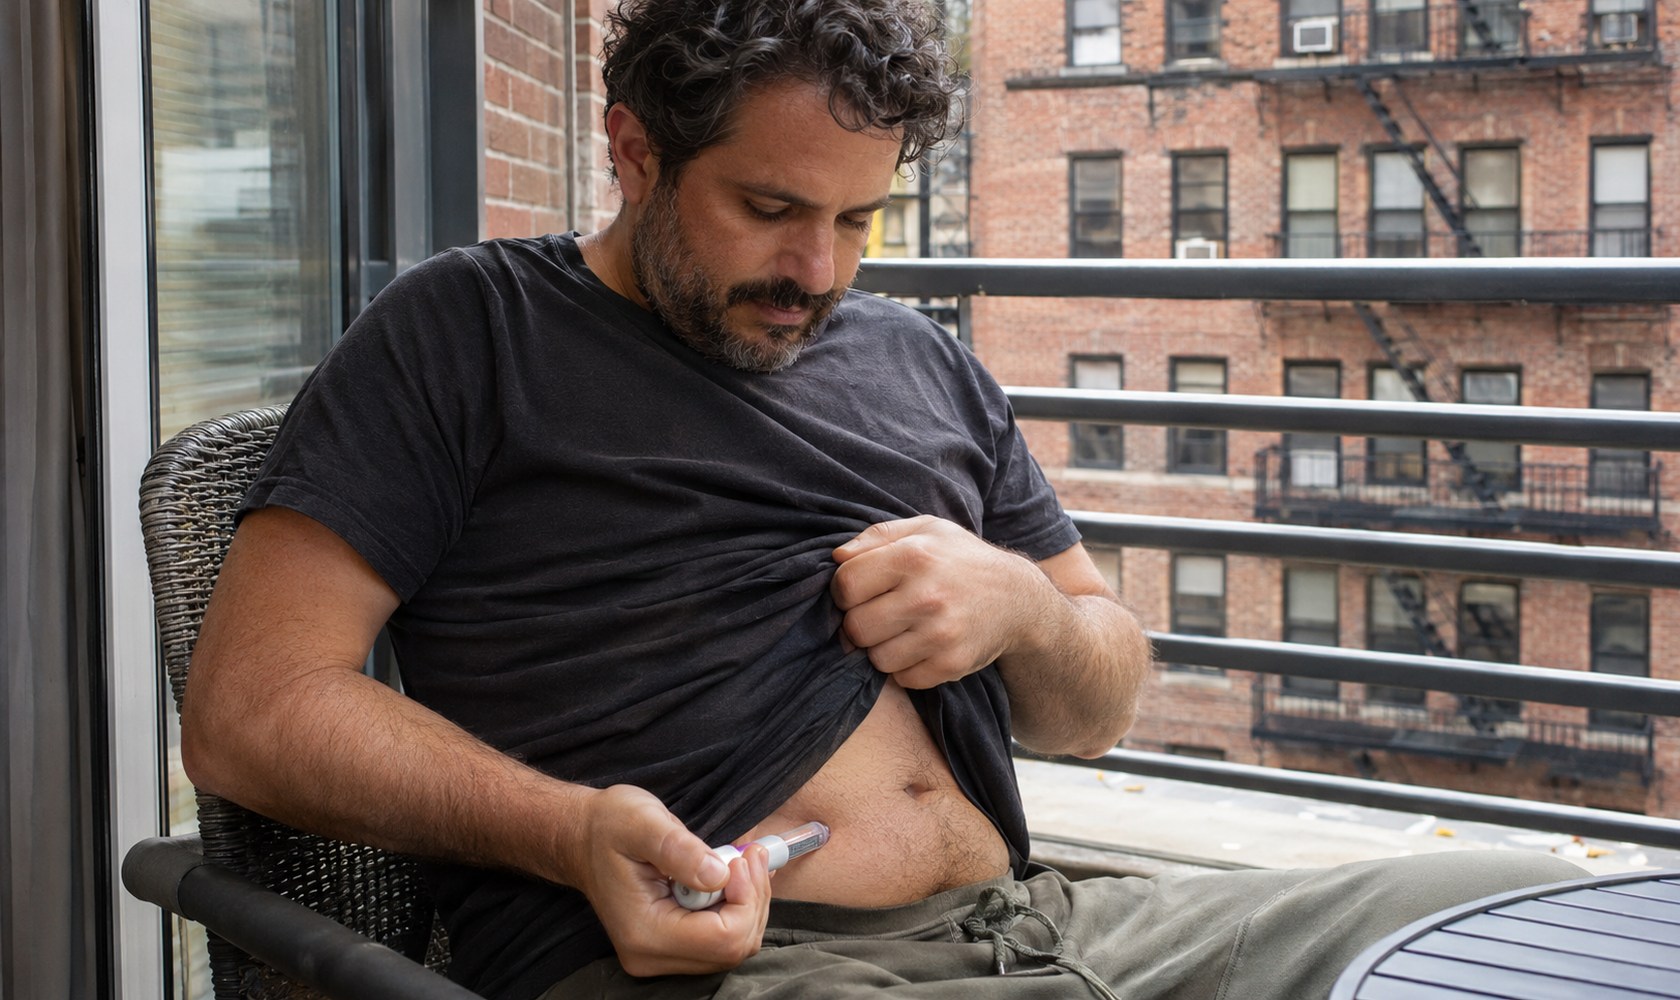
Learn the injection or tablet technique from the pharmacist or prescribing team. Devices can differ in concentration, dose selection, preparation, and storage. Never estimate a dose from an online photograph or a number of clicks intended for another device.
Keep injections in the conditions stated on the label and do not share pens, even if a needle changes. Ask how to dispose of needles safely. For oral products, confirm food, water, and timing requirements rather than treating the tablet like any other daily medicine.
A missed dose has product-specific instructions. Check them before taking a delayed dose or moving the schedule. Repeated access problems deserve a conversation about a workable plan instead of repeated unsupervised stopping and restarting.
Put broader health claims in context
Some products have evidence and approvals for additional cardiovascular, kidney, or other outcomes in defined patient groups. Those benefits belong to the specific product, indication, and evidence; they do not establish that every GLP-1 medicine prevents every related condition.
Research associations involving dementia or cancer are not the same as a prescription indication or proof of prevention. Ask which benefit applies to your own diagnosis and which questions remain under study. The immediate treatment decision should rest on established needs, expected benefit, risks, and the follow-up you can maintain.
Sources
- National Institute of Diabetes and Digestive and Kidney Diseases. Prescription Medications to Treat Overweight and Obesity. https://www.niddk.nih.gov/health-information/weight-management/prescription-medications-treat-overweight-obesity
- Novo Nordisk. Ozempic prescribing information. https://www.novo-pi.com/ozempic.pdf
- Novo Nordisk. Wegovy prescribing information. https://www.novo-pi.com/wegovy.pdf
Related reading
- Prescription Weight Loss Medications: Comparing the Options
- Ozempic vs. Wegovy: What the Shared Ingredient Does Not Tell You
- Health Guide
Medical Disclaimer: This content is provided for informational and educational purposes only and does not constitute personalized medical advice, diagnosis, or treatment. Always consult a qualified physician or licensed healthcare provider with any questions regarding a medical condition or prescription medication. Read our Editorial & Medical Review Policy.