
Xulane Birth Control Patch: Weekly Use, Application and Safety Limits

Xulane delivers norelgestromin and ethinyl estradiol through a patch on the skin. It replaces the daily pill task with a weekly change during the active part of the cycle. The patch still contains estrogen, and the delivery route does not remove the need for a safety review.
Check eligibility first. Body mass index, smoking, clotting history and other medical factors can rule out this product or change whether it fits. The decision concerns more than whether you prefer a patch to a tablet.
How the patch prevents pregnancy
Xulane combines a progestin with an estrogen, placing it in the combined hormonal contraceptive category. The hormones mainly suppress ovulation and also change cervical mucus. They enter the bloodstream through the skin rather than through a swallowed tablet.
Continuous release helps explain the weekly schedule, but it does not mean that the dose can continue indefinitely after a patch becomes detached or overdue. Correct adhesion, change dates and the patch-free interval all contribute to the method's use.
Because the patch does not rely on absorption from the stomach, vomiting does not create the same tablet-absorption issue as it can with oral contraception. Illness can still disrupt the application schedule, however. Check the patch and its timing even when you feel unwell.
The patch does not protect against sexually transmitted infections. Condoms can address that separate concern and may also provide temporary backup when the instructions require it. A contraceptive prescription does not answer every sexual-health question.
What a weekly method offers and what it does not
A weekly action can fit someone who repeatedly forgets daily tablets. It also lets you see whether the patch remains in place. You still need a change-day routine, access to the next supply and a plan for travel or other disruptions.
Some patients using combined hormonal contraception experience lighter bleeding or fewer cramps. Individual responses differ. A clinician should discuss a specific symptom goal rather than promise that every patch user will have the same benefits.
Xulane's contraceptive indication does not make it a menopause hormone treatment or an automatically approved acne treatment. Do not transfer a benefit or indication from another hormonal product solely because both contain estrogen and a progestin.
Compare the patch with other options in terms of both health and daily life. Skin irritation, visible placement, the need for adhesion and the estrogen-related assessment may matter as much as the convenience of weekly changes.
The labeled four-week cycle
Apply one new patch each week for three weeks, then have one patch-free week. Apply the next patch on schedule after that interval. Keep the same change day, wear only one patch at a time and do not extend the patch-free period beyond the instructions.
A withdrawal bleed may occur during the patch-free week, but bleeding does not decide when to begin the next cycle. Start on the scheduled day even if bleeding continues, unless a clinician directs a change for a specific reason.
The starting plan can vary with menstrual timing, prior contraception and pregnancy circumstances. Ask the prescriber when to apply the first patch and whether to use temporary backup. Do not assume that every new user has protection immediately after application.
Application and placement
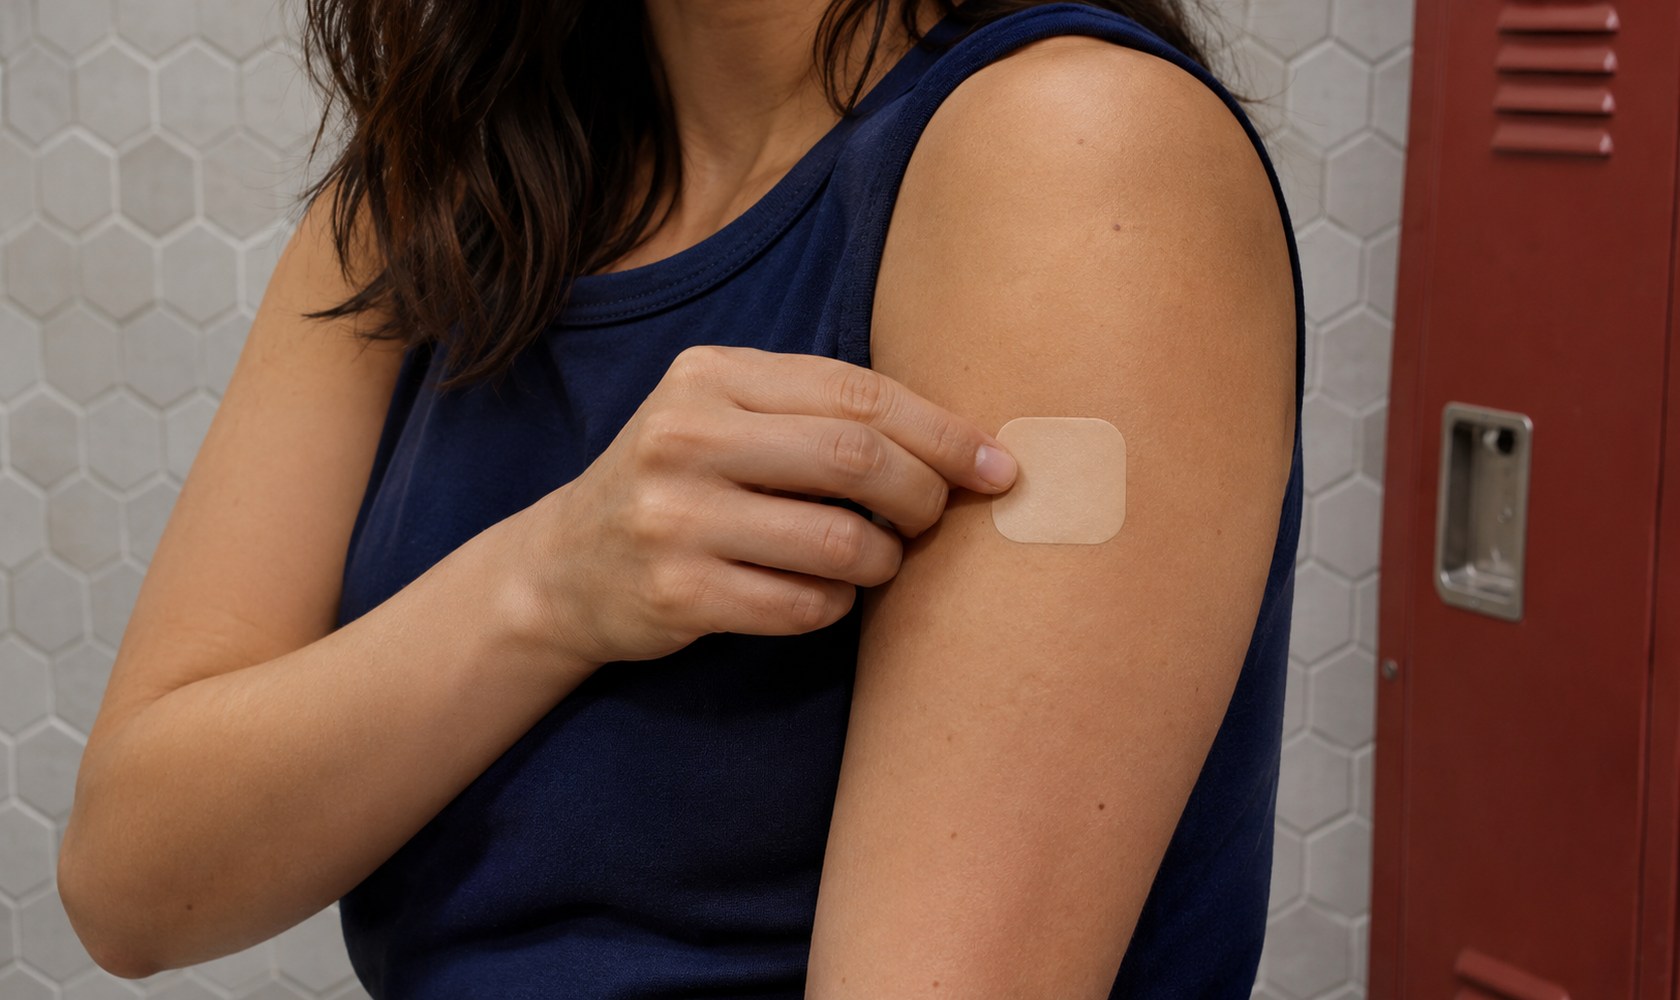
The labeled sites include the upper outer arm, abdomen, buttock and back. Choose intact skin and follow the leaflet's preparation instructions. Avoid a site where tight clothing or another source of friction could repeatedly disturb the patch.
Apply the patch promptly after removing it from its pouch. Press it into place as directed and check that its edges adhere. Do not cut, alter or layer patches to change the delivered amount of medicine.
Keep lotions, oils or other products away from the application area when the instructions advise it. They can interfere with adhesion. Ask about a skin condition or a rash before repeatedly applying another patch to irritated skin.
Check the patch during ordinary use. Bathing, exercise or a busy schedule can make it easy to miss an edge lifting or a detachment. A visible patch can still require action if it no longer lies securely against the skin.
A loose patch or a late change needs its own instructions
The response depends on whether the issue involves detachment, an overdue replacement or a delayed start after the patch-free week. The duration and cycle week matter. Do not apply a general claim that the patch always works for two extra days.
Use the Xulane leaflet and tell the pharmacist when the problem began. If you cannot establish how long the patch has been off, explain that uncertainty. Ask whether to apply a new patch, change the cycle schedule or use backup protection.
Do not secure an unreliable patch with improvised tape as a substitute for the product instructions. A clinician or pharmacist can explain how to replace it and what the interruption means. If unprotected sex occurred during a possible lapse, ask promptly about emergency contraception.
Common effects to discuss at follow-up
Possible effects include breast discomfort, nausea or vomiting, headache, abdominal symptoms, spotting and changes in bleeding. Some patients report mood changes. Redness, itching, pain or a rash can occur where the patch touches the skin.
Keep a record of which site you used and when a skin reaction appeared. Explain whether the patch stayed attached and whether the symptom returned with another application. A persistent rash can need assessment rather than repeated changes of location alone.
Tell the clinician about symptoms that worsen or make it difficult to continue using the method. Do not assume that any severe headache belongs to a normal adjustment phase. Describe new neurological symptoms, visual changes or an unusual pattern.
Clot risk, body mass index and other limits
Xulane's label contraindicates use at a BMI of 30 or higher. It also warns that contraceptive effectiveness may be lower at a body weight of 198 pounds, or 90 kilograms, or more. These are different statements: one concerns a safety limit and the other concerns effectiveness.
The product also contraindicates use in people over 35 who smoke cigarettes. A previous clot, stroke, certain cardiovascular conditions, liver disease, hormone-sensitive cancer or unexplained uterine bleeding can make the patch unsuitable. Review the full history with the prescriber rather than choosing solely on convenience.
Skin delivery changes hormone exposure compared with some oral products. Do not interpret the route as proof that the patch creates a lower clot risk. The clinician should compare the actual products and the risk factors that apply to you.
Report pregnancy concerns, recent childbirth, breastfeeding, planned surgery and periods of limited movement. These circumstances can change the contraceptive plan. Mention other medicines and supplements so the clinician can review interactions as well.
Symptoms that need urgent action
Sudden shortness of breath, chest pain, one-sided leg pain or swelling, sudden loss of vision, weakness, numbness or difficulty speaking require urgent assessment. Call 911 for emergency symptoms. Tell the care team that you use an estrogen-containing contraceptive patch.
Yellowing of the skin or eyes, severe abdominal pain or another major new symptom also needs prompt medical review. A routine side-effect appointment should not delay care when the symptom suggests a serious problem.
Storage and supplies for the next cycle
Keep unused patches in their protective pouches at the labeled room temperature, commonly 68-77 degrees Fahrenheit or 20-25 degrees Celsius. Read the supplied leaflet for the complete storage instructions. Avoid heat, damaged packaging and access by children or pets.
Arrange enough supply for the next scheduled cycle and ask what to do if a replacement becomes necessary early. Confirm the change day, backup instructions and contact details before a problem occurs. Keep the product leaflet with the patches rather than relying on a remembered rule for another method.
Tell the clinician if the practical demands remain difficult after a trial. Repeated late changes, uncomfortable application sites or persistent detachment can justify comparing another contraceptive. A different method should come with a transition plan that covers the interval between the last patch and the replacement.
Sources
- DailyMed. Xulane: norelgestromin and ethinyl estradiol patch. Prescribing information. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f7848550-086a-43d8-8ae5-047f4b9e4382
- Centers for Disease Control and Prevention. Combined Hormonal Contraceptives. https://www.cdc.gov/contraception/hcp/usspr/combined-hormonal-contraceptives.html
- Centers for Disease Control and Prevention. U.S. Medical Eligibility Criteria for Contraceptive Use, 2024. https://www.cdc.gov/mmwr/volumes/73/rr/rr7304a1.htm
Related reading
- Sprintec Birth Control: Tablet Schedule, Uses, Side Effects and Precautions
- Yasmin Birth Control: Ingredients, Benefits, Risks and Daily Use
- Health Guide
Medical Disclaimer: This content is provided for informational and educational purposes only and does not constitute personalized medical advice, diagnosis, or treatment. Always consult a qualified physician or licensed healthcare provider with any questions regarding a medical condition or prescription medication. Read our Editorial & Medical Review Policy.